 Skip to content


You got the ultrasound. Clean. You saw the urologist. Nothing. Bloodwork, normal. And the pain is still there. Pulling, aching, sometimes sharp when you lift, twist, or push through a hard set at the gym. An occult inguinal hernia, also called a hidden hernia, is a small abdominal wall defect that can cause groin and testicular pain without a visible bulge or anything obvious on routine imaging. This is one reason it can be missed in men with otherwise unexplained testicular pain.
Chronic testicular pain, sometimes called chronic orchialgia or chronic scrotal pain, does not always originate in the testicle itself. Nerves, muscles, the abdominal wall, hip, pelvic floor, and inguinal canal can all refer pain into the same area.
If you’ve been told your workup is “normal” but you know something isn’t right, the next step may be looking beyond the testicle itself.
Quick answer: Can an occult hernia cause testicular pain?
Yes. An occult inguinal hernia can cause testicular or groin pain without a visible bulge. It happens when symptoms worsen with lifting, twisting, coughing, bearing down, sprinting, or exercise.
This page explains why hidden hernias can be missed on routine exams and imaging. We will discuss how Pelvis NYC uses a load-based physical therapy assessment to identify suspicious mechanical patterns. How Manhattan Pain Medicine can help determine whether the pain is coming from a small inguinal defect, an irritated nerve, the psoas, or another nearby structure.
That distinction matters because the testicle may be where the pain is felt without being where the problem originates.
Unexplained groin or testicular pain after a normal workup? Book a free 15-minute teleconsultation with Dr. Adam. No referral needed to get started at our Chelsea, NYC clinic.Sudden or severe testicular pain is different from the chronic pattern discussed in this article and should be evaluated promptly to rule out urgent causes.
What is an occult inguinal hernia and why can it cause testicular pain?
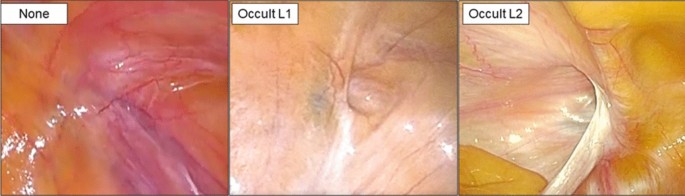
An occult inguinal hernia occurs when tissue pushes through a small weak point in muscle or connective tissue around the inguinal canal.
The inguinal canal is a passage through the lower abdominal wall containing structures and nerves that travel toward the groin and genital region. Unlike a typical inguinal hernia, an occult hernia may be too small or positional to create an obvious bulge.
It may become more apparent only when abdominal pressure increases during standing, lifting, coughing, straining, or a Valsalva maneuver.
Small amounts of fat or other tissue may move through the defect without producing the classic appearance most people associate with a hernia.
The reason this can cause testicular pain is anatomical.
The ilioinguinal, iliohypogastric, and genitofemoral nerves travel through or near this region. Irritation of these nerves can create aching, burning, pulling, sharp, or radiating pain that is perceived in the groin or testicle.
One of the more counterintuitive clinical patterns is that a very small defect can sometimes be disproportionately painful.
A larger opening may allow tissue to move with relatively little resistance. A small fascial opening can create a tighter environment around fat, fascia, and nearby nerves. It produces a combination of local pressure, neuropathic irritation, and protective abdominal muscle guarding.
That guarding can eventually become another source of pain.
Why can an occult hernia be missed on ultrasound, CT, or MRI?
Most men with chronic testicular or groin pain go through a similar diagnostic loop before reaching an answer.
Understanding why a routine workup can be normal is important.
| Test | What it checks | Why the source may still be missed |
| Urological exam and Doppler ultrasound | Testicular structure, blood flow, torsion, masses | The pain may originate outside the testicle |
| Standard scrotal or groin ultrasound | Superficial tissue and visible hernias | A small defect can be positional or load-dependent |
| Bloodwork and STI screening | Infection and inflammation | Nerve and musculoskeletal causes may produce no abnormal blood markers |
| Standard physical exam | Bulges, tenderness, reflexes | A static examination may not reproduce symptoms that occur under load |
At our clinic, we regularly see men who have already been evaluated by multiple specialists without a clear explanation for the pain.
Sometimes the issue is not that the wrong tests were performed. The body was simply being examined under different conditions from those that trigger the symptoms.
How are CT and MRI performed?
Most CT and MRI studies are performed with the patient lying flat. An occult inguinal defect that changes with position or abdominal pressure may therefore be less apparent than it is while the patient is standing, lifting, or bearing down.
When Pelvis NYC’s examination raises suspicion for a hidden hernia, Manhattan Pain Medicine can add a medical and interventional perspective to the workup. Dynamic ultrasound with Valsalva can be useful when the goal is to watch what happens in the inguinal region as abdominal pressure changes.
Dynamic ultrasound has also been supported as a useful first or confirmatory imaging approach when an occult inguinal hernia is suspected.
But imaging alone is not the entire diagnosis.
A small inguinal defect can be present without necessarily explaining the patient’s pain. The imaging findings have to make sense alongside the symptoms, physical examination, and response to diagnostic testing.
How Pelvis NYC evaluates hidden hernia and chronic testicular pain

Pelvis NYC’s examination is built to identify mechanical patterns that may not appear during a short, static clinical examination.
Instead of only examining the abdomen at rest, we look at what happens to the inguinal canal, abdominal wall, pelvic floor, hip, and associated nerve pathways when the body is actually loaded.
Step 1. Load-based abdominal wall assessment
We assess symptoms during Valsalva, single-leg stance, rotational movement, abdominal loading, and other positions that reproduce the patient’s pain.
A hidden hernia may become symptomatic only when abdominal pressure rises.
Patients may also describe tenderness or pulling in the groin, lower abdomen, or upper thigh that increases with prolonged standing, lifting, coughing, or exercise.
Step 2. Nerve-specific palpation
We assess the anatomical pathways of the ilioinguinal, iliohypogastric, and genitofemoral nerves.
If pressure over a particular area reproduces the same pulling, aching, burning, or sharp sensation the patient recognizes from the groin or testicle, that gives us an important clue about which pathway may be involved.
It does not establish the diagnosis by itself.
The pattern becomes more meaningful when it matches the patient’s history, movement triggers, and other examination findings.
Step 3. Pelvic floor and hip mechanics
Chronic pain around the inguinal region can cause the body to protect itself.
The pelvic floor, hip adductors, abdominal wall, and other surrounding muscles may remain tightened long after the original trigger.
That secondary guarding can contribute to pelvic pain, groin pain, lower abdominal pain, and sometimes symptoms extending toward the hip or lower back.
We assess these patterns as part of the pelvic floor and orthopedic physical therapy evaluation.
The hip is particularly important because some patients can experience symptoms that closely resemble a hidden hernia even when no hernia is found.
When that happens, the anatomical search needs to move higher.
Step 4. Movement and injury history
Many patients can trace the beginning of symptoms to a particular period of physical stress.
It may follow heavy lifting, a hard pivot, a new training program, repetitive abdominal loading, chronic coughing, constipation and straining, or an injury that never completely settled down.
At our clinic, we frequently see active men and NYC professionals who continued training or working through the symptoms because there was no obvious injury or visible hernia.
Reconstructing that timeline can help identify what was happening mechanically when the pain began.
Step 5. Targeted manual therapy and load progression
Physical therapy can address nerve mobility, pelvic floor and hip guarding, abdominal wall function, and progressive tolerance to loading.
For some patients, that resolves the problem.
For others, persistent neuropathic symptoms, recurrent pain under load, prior surgery, or concern for an occult structural defect suggest that another layer of diagnostic information is needed.
This is where collaboration with Manhattan Pain Medicine becomes useful.
Pelvis NYC can identify how the symptoms behave during movement. Manhattan Pain Medicine can help determine which anatomical structure is producing that response.
Related Blog: Hernia Treatment Intervention With Physical Therapy
How Manhattan Pain Medicine confirms the source of testicular and groin pain
At Manhattan Pain Medicine, Dr. Jason W. Siefferman approaches these cases by asking a more specific question than whether a hernia is simply present:
Which structure is generating the patient’s familiar pain, and where along the nerve pathway is the irritation occurring?
A small occult inguinal hernia, local nerve compression, irritation of the genitofemoral nerve higher in the pelvis, post-surgical scar tissue, hip pathology, and secondary abdominal wall guarding can produce overlapping symptoms.
That is why the examination, imaging, and response to targeted diagnostic procedures need to be considered together.
Step 1. Diagnostic ilioinguinal and genitofemoral nerve blocks
An ultrasound-guided diagnostic block can place a small amount of local anesthetic around a suspected nerve, such as the ilioinguinal or genitofemoral nerve.
The response helps localize the pain generator.
If the patient’s familiar groin or testicular pain decreases substantially while that pathway is anesthetized, nerve involvement becomes more likely.
If the expected area of skin becomes numb but the patient’s deeper testicular pain remains, the problem may be occurring farther upstream.
In that sense, a diagnostic block is not simply being used to temporarily relieve pain.
The response itself is part of the diagnostic information.
Nerve blocks are recognized as useful tools for identifying implicated nerves in neuropathic groin and testicular pain, particularly after inguinal hernia surgery.
Step 2. The psoas and genitofemoral nerve: a hidden hernia mimic
The genitofemoral nerve does not begin in the groin.
It originates from the upper lumbar region and passes through the psoas muscle before traveling toward the inguinal canal and genital region.
This creates an important source of referred testicular pain.
If hip instability, a labral injury, or another painful hip condition causes the psoas to remain chronically contracted, that muscle can irritate the nerve as it passes through it.
The result can be a persistent pulling or aching sensation in the testicle that feels very similar to an inguinal hernia.
Chronic testicular pain is known to have possible sources outside the scrotum, including the pelvic floor, hip, spine, and peripheral nerves.
When the examination suggests a more proximal source, a targeted diagnostic procedure can help determine whether reducing the psoas-related irritation changes the familiar testicular symptoms.
Step 3. Treatment follows the confirmed mechanism
Once the likely pain generator has been identified, treatment becomes more specific.
Constipation and abdominal pressure. Repeated straining can continuously increase intra-abdominal pressure and aggravate an already sensitive inguinal region. Addressing bowel function can therefore be an important part of the treatment plan when constipation is present.
Post-surgical nerve entrapment. Testicular or groin pain after inguinal hernia repair may involve the ilioinguinal, iliohypogastric, or genitofemoral nerves. Scar tissue or mesh can contribute to irritation or restriction around these structures.
In selected cases, ultrasound-guided hydrodissection may be considered to separate a nerve from surrounding tissue and improve mobility around it.
Psoas-related nerve irritation. When persistent psoas overactivity appears to be contributing to genitofemoral nerve irritation and physical therapy has plateaued, targeted treatment may be considered. Selected patients may be candidates for botulinum toxin treatment, followed by rehabilitation directed at the hip and movement mechanics that created the guarding pattern.
Persistent peripheral nerve pain. When a specific peripheral nerve has been clearly identified and diagnostic blockade has been helpful, longer-lasting nerve-directed procedures may sometimes be considered in appropriately selected patients.
The objective is not simply to suppress the sensation of pain.
It is to reduce the confirmed pain generator enough to allow the mechanical problem and functional consequences around it to be addressed.
Step 4. When does an occult inguinal hernia need surgery?
Finding a hidden inguinal hernia does not automatically mean that surgery is necessary.
The important question is whether the structural defect actually explains the patient’s symptoms.
Surgical evaluation becomes more compelling when the location of the defect, symptom pattern, physical examination, dynamic imaging, and diagnostic testing point toward the same source.
When that happens, Manhattan Pain Medicine can coordinate evaluation with a surgeon experienced in inguinal hernia and pelvic pain.
Minimally invasive approaches are commonly used for inguinal hernia repair, although the appropriate surgical technique depends on the individual patient and anatomy.
Recent research reinforces why matching the imaging finding to the symptoms matters. Patients with occult inguinal hernias can improve after repair, but not every radiologically detected defect necessarily requires immediate surgery.
The goal is to identify the patient whose hernia is causing the pain, not simply the patient who happens to have a hernia.
Step 5. Returning to physical therapy after treatment
Treating the primary pain generator is not always the end of recovery.
Months or years of pain can change how someone moves.
The abdominal wall may continue guarding. The pelvic floor can remain tense. The hip may avoid load. The patient may unconsciously change how they lift, walk, train, sit, or brace.
This brings the patient back to Pelvis NYC to progressively restore abdominal wall loading, pelvic floor coordination, hip mechanics, mobility, strength, and confidence with exercise.
If the original symptoms recur during rehabilitation, that information can also be communicated back to Manhattan Pain Medicine and used to reassess the pain mechanism rather than automatically repeating treatment.
That feedback loop is the core of the collaboration.
Why does early diagnosis matter for occult hernia and chronic groin pain?
The longer testicular or groin pain continues, the more the surrounding system can adapt to it.
Protective muscle guarding may increase. The pelvic floor may tighten. Nerves can become increasingly sensitive. Movement patterns change.
Eventually, secondary symptoms may persist even after the original trigger has been addressed.
Early evaluation does not mean rushing toward an invasive treatment.
It means identifying whether the problem is primarily structural, neurological, muscular, pelvic-floor related, or a combination before those compensations become more established.
For active men in New York City, whether training, competing in sports, or simply trying to work without persistent groin or testicular pain, that distinction matters.
Frequently asked questions about occult hernia and testicular pain
Can an occult inguinal hernia cause testicular pain without a bulge?
Yes. An occult inguinal hernia can produce groin or referred testicular pain without creating a visible bulge.
Because the defect can be small or position-dependent, symptoms may become more noticeable during lifting, standing, coughing, exercise, or bearing down.
Can a normal ultrasound miss an inguinal hernia?
It can.
Occult hernias can be difficult to identify, and ultrasound results depend partly on the examination technique and examiner experience. Dynamic assessment and Valsalva may improve the ability to identify a suspected defect.
When clinical suspicion remains high despite negative imaging, additional medical evaluation may be appropriate.
Can an inguinal hernia cause chronic testicular pain?
Yes, but a hernia is only one potential cause.
The ilioinguinal and genitofemoral nerves, pelvic floor, hip, lumbar region, prior hernia surgery, and other structures can also refer pain into the testicle.
That is why identifying the actual pain generator matters.
What’s the difference between a hidden hernia and a regular inguinal hernia?
A typical inguinal hernia often creates a visible or palpable bulge.
A hidden or occult inguinal hernia may be smaller and may only become apparent when abdominal pressure increases or the body is placed under load.
Do all occult inguinal hernias require surgery?
No.
A small defect on imaging does not automatically establish that the hernia is responsible for the patient’s symptoms.
Treatment depends on whether the hernia correlates with the clinical pattern and whether other causes of groin or testicular pain have been identified.
What if I have testicular pain but no hernia is found?
The evaluation should broaden rather than stop.
The genitofemoral nerve travels through the psoas muscle before reaching the groin. Pelvic floor tension, hip pathology, abdominal wall pain, nerve entrapment, and referred pain from the spine can also produce symptoms that are felt in the testicle.
Can physical therapy help chronic testicular or groin pain?
Physical therapy may be appropriate when pelvic floor dysfunction, hip mechanics, abdominal wall guarding, musculoskeletal dysfunction, or nerve mobility contribute to the pain.
Pelvis NYC evaluates these factors under movement and load rather than looking only at the location where the pain is felt.
Do I need a referral to see Pelvis NYC for testicular or groin pain?
No referral is required.
New York State’s direct access law allows patients to begin a physical therapy evaluation without first obtaining a physician referral.
Unexplained testicular pain isn't always unexplained. Sometimes the source simply hasn't been identified yet. Schedule your first appointment at Pelvis NYC or call (929) 590-3445.Dr. Adam Gvili, PT, DPT
Dr. Adam Gvili is the founder and lead clinician at Pelvis NYC, a pelvic floor and orthopedic physical therapy clinic. He specializes in male pelvic health, chronic groin and testicular pain, occult hernia assessment, and orthopedic rehabilitation. He has been featured in Bloomberg, Business Insider, and Experience Life magazine.
Clinical collaboration: Jason W. Siefferman, MD
Dr. Jason W. Siefferman is the Founder and Medical Director of Manhattan Pain Medicine. He is triple board-certified in Physical Medicine and Rehabilitation, Pain Medicine, and Headache Medicine. His clinical approach focuses on identifying the anatomical pain generator and coordinating treatment across overlapping nerve, musculoskeletal, pelvic, and other pain mechanisms.
This article is for educational purposes and does not replace individualized medical evaluation. Persistent testicular, groin, or abdominal pain should be evaluated by an appropriate healthcare professional. Sudden or severe testicular pain warrants prompt medical assessment.


